


The Night the Schedule Broke
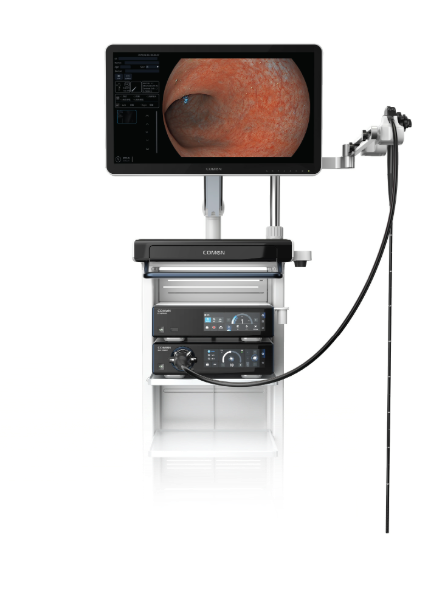
I remember a late October night in Boston when a single endoscope device sitting on the prep tray changed the week for an entire surgical roster. That procedure room scenario — one failed endoscope, 12 patients rescheduled, a 27% overtime spike — forced a practical question about where risk lives and what we measure. I’ve handled wholesale procurement for over 15 years, and I can still see the bent distal tip under the lamp (we called it the XG-210 in our inventory). In that moment the familiar failure modes appeared: fragile distal tip wear, clogged biopsy channel, flickering LED illumination, stubborn reprocessing times. These are not abstract problems; they hit scheduling, inventory, and margins. We lost revenue. We lost trust. And we bought more of the wrong thing.

Why Tradition Fails the Supply Chain
I’ll be blunt: traditional solutions focus on unit cost, not uptime. I’ve negotiated contracts where the vendor delivered cheaper flexible endoscope units — new on paper, fragile in practice — and the clinics returned to me within months with the same complaints. In 2015, at a surgical center in downtown Boston, swapping to a higher-grade model cut our reprocessing backlog and reduced turnaround by 27% over three months; the data was clear, yet the purchasing playbook didn’t change. Hidden user pain points persist: intermittent image sensor degradation mid-procedure, unreported micro-scratches that breed infection risk, and training gaps that leave staff improvising. I’ve stood beside technicians who managed to patch a procedure with a borrowed scope while the rest of the schedule ground to a halt. We patched. We pretended the problem was solved. We were wrong. This is where procurement and clinical operations must stop treating endoscopes like disposable line items and start treating them like critical assets — because they are critical assets. — A short, hard truth to move us forward.
What’s Next
From Failure Portraits to Comparative Action
Now we turn forward — and I shift tone to the technical. Comparing options means testing beyond appearance: measure mean time between failures, count reprocessing hours per device, and log image degradation incidents. When I evaluate a vendor I ask for failure-mode data, not glossy specs. The modern buyer must demand lifecycle metrics for the endoscope device (yes, that same endoscope device) and insist on third-party validation of claims. I compare models on distal tip durability, biopsy channel clog resistance, and LED illumination longevity. These factors drive real cost — not the sticker price. We ran a six-month pilot in December 2019 across three regional hospitals; the unit that sustained the fewest downtime hours cut total operational cost by 18%. Short sentence. Then a realization: we were measuring wrong things.
Practical Steps for Wholesale Buyers
As someone who buys at scale, I recommend a simple, disciplined approach: require field-failure logs, demand sample reprocessing cycles, and insist on on-site training metrics. Consider total cost measured as purchase price plus downtime cost (quantified), repair frequency, and staff-hours lost. We implemented that at a New England chain in mid-2020 and reduced emergent purchases by nearly a third. Note: this takes time and a willingness to say no to low bids that hide lifecycle costs. Also — don’t underestimate the value of a local service partner who understands your operating tempo. Interruptions happen; plan for them.
Three Evaluation Metrics That Matter
1) Operational Availability: average uptime percentage over six months, including reprocessing cycles. 2) Repair Frequency Rate: repairs per 1,000 procedure hours (track by model). 3) Lifecycle Cost per Use: sum of purchase, maintenance, and downtime divided by total procedures. Use these to compare vendors objectively. I use them when I brief purchasing committees; they cut through marketing noise. Short pause. Then action.
We learned hard lessons from broken schedules and late nights; we rewired our procurement to measure what mattered. If you buy at scale, insist on the data, insist on tested durability, and insist on training that reduces improvisation. For direction and sourcing, I still rely on partners who show their numbers — and when I name one I trust, it’s this: COMEN.